Clinical guide · Direct restorative and adhesion
Post-operative sensitivity after composite restorations: causes and a prevention checklist
In this article7
In short
Most post-operative sensitivity after a composite is technique, not material: over-etched or dried-out dentine, a gap under the restoration from shrinkage stress, an under-cured base, or a high spot. Prevent it with isolation, a short dentine etch and moist bonding, a liner or desensitiser on deep dentine, increments or a bulk-fill that cures to depth, and an occlusal check before the patient leaves.
- Reported rates of post-operative sensitivity after posterior composites vary widely between studies; Class II restorations and deep cavities carry the highest risk.
- Dentine etched with phosphoric acid for longer than about 15 seconds is demineralised deeper than the adhesive can infiltrate, which leaves exposed collagen and open tubules.
- Polymerisation shrinkage stress pulls the composite away from the pulpal floor when the bonded surface is large and the increment is thick; that gap moves fluid in the tubules on cold and bite.
- Resin-modified glass ionomer liners bond to dentine and cure in a thin layer, sealing tubules under the composite without the solubility of plain calcium hydroxide.
- A high spot on a new composite is the most common cause of pain on biting and the fastest to fix.
More key facts+3
The problem: the call two days later
The restoration looked good, the margins were clean, the patient left comfortable. Two days later the tooth hurts on cold, or on biting, or both. Post-operative sensitivity is the most common complication of a composite restoration and one of the hardest to explain to a patient, because the filling itself looks perfect. In almost every case the cause is one of a short list of technique errors, and each has a specific prevention.
This guide goes through those causes one by one, gives the fix for each, and names the class of material that helps. It ends with a chairside checklist you can print.
Understand: the causes, in order of how often they happen
1. A high spot
Pain on biting that starts the moment the anaesthetic wears off is occlusion until proven otherwise. A composite that is even a fraction high concentrates the whole bite on one cusp, and the ligament complains within hours. Practice: check with thin articulating paper in centric and excursions before the patient leaves; a second check a week later costs nothing.
2. Over-etched or over-dried dentine
Phosphoric acid on dentine for too long demineralises deeper than the adhesive can penetrate. The resin never reaches the bottom of the demineralised zone, and the exposed collagen and open tubules respond to cold and air. Blasting the dentine dry collapses the collagen so the adhesive cannot infiltrate it at all. Practice: etch dentine for no more than about 15 seconds when etch-and-rinse is used, or use selective enamel etching with a universal adhesive; leave dentine visibly moist; scrub the adhesive in; evaporate the solvent gently.
3. A gap at the pulpal floor
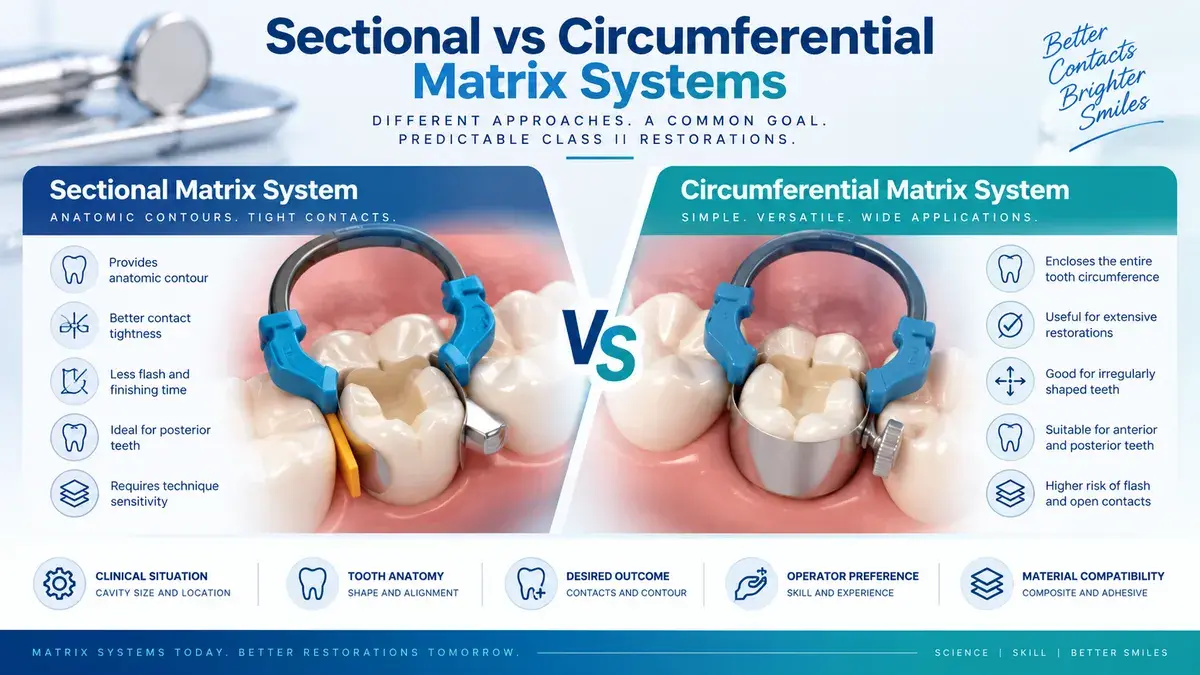
Composite shrinks as it cures and the shrinkage pulls on the bond. In a deep box with bonded walls on every side, the weakest bond, usually the pulpal floor, lets go, and a gap forms that fluid moves through on every temperature change. Practice: smaller increments, a flowable or resin-modified glass ionomer liner on the deepest dentine, a bulk-fill material designed for the depth, and soft-start curing where your light supports it.
4. Under-cured composite or adhesive
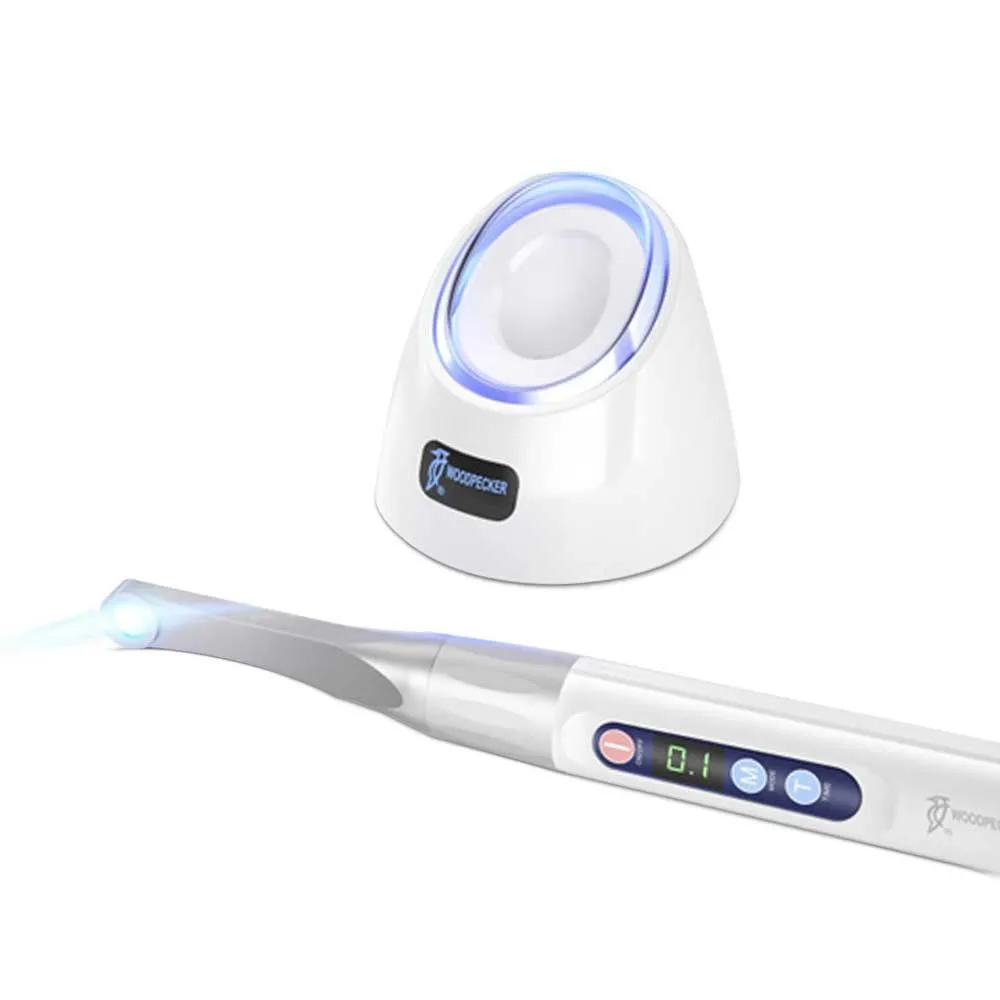
A light held at a distance, a scratched tip, a battery at the end of its charge, or a bulk-fill placed deeper than its stated depth of cure leaves soft material at the base. Uncured monomer irritates the pulp and the restoration flexes. Practice: know your light's output, cure with the tip as close and as perpendicular as the cavity allows, and cure through the buccal and lingual walls of a deep box as well as from the occlusal.
5. Contamination
Saliva, blood or gingival fluid on etched enamel or primed dentine ruins the bond invisibly. Practice: rubber dam, or at least a dry field with retraction and a fresh cotton roll; re-etch enamel if it is contaminated. Ask about latex allergy before placing the dam and use a non-latex sheet if needed.
6. Deep caries close to the pulp
Sometimes the pulp was already inflamed. A deep cavity, a history of lingering pain, or a tooth that was sensitive before treatment predicts sensitivity after it regardless of technique. Practice: test vitality before treating deep lesions, warn the patient, protect the deepest dentine with a liner or a calcium-silicate material, and record the finding.
7. Cracked tooth
A cusp that was already cracked will hurt on release of biting pressure after any restoration. Practice: bite test each cusp on a tooth with a large old restoration before you replace it.
What the evidence says
- Evidence. Systematic reviews report no significant difference in post-operative sensitivity between bulk-fill and incrementally placed posterior composites.3
- Evidence. In cervical lesions, selective enamel etching with a universal adhesive improved retention compared with self-etch alone, without the dentine over-etching that total-etch invites.4
- Practice. Clinical reviews on the topic consistently rank operator technique (etching, drying, curing, occlusion) above the choice of composite as the source of sensitivity.1, 2
Options: what helps, by class
| Class | What it does | Stocked examples |
|---|---|---|
| Resin-modified glass ionomer liner | Seals tubules on deep dentine, bonds to dentine, releases fluoride, cures in a thin layer | Fusion iSeal LC, Ionoseal, Biner LC |
| Desensitiser | Occludes tubules or reduces nerve response; used on deep dentine, after bleaching, or in sensitive patients | Shield Activ (HEMA-based), UltraEZ (potassium nitrate and fluoride), CharmSensy (light-curing) |
| Low-stress bulk-fill | Cures to 4 mm with reduced shrinkage stress on the pulpal floor | SDR Plus |
| Universal adhesive with selective etch | Avoids over-etching dentine while keeping the enamel bond | See the adhesives guide |
| Curing light with adequate output | Cures the adhesive and every increment to depth | Woodpecker i LED Plus, VALO Grand |
| Isolation | Keeps the field dry from etch to final cure | Rubber dam sheets, clamps and frames |
| Articulating paper | Finds the high spot before the patient does | Thin 50 µm paper, horseshoe 100 µm |
Shop the categories in this guide
Compare: cause, sign, fix
| Cause | How it presents | Prevention step | Material that helps |
|---|---|---|---|
| High spot | Pain on biting from day one | Occlusal check in centric and excursions | Articulating paper |
| Over-etched dentine | Sharp cold sensitivity, air sensitivity | Dentine etch under 15 s, or selective enamel etch; moist bonding | Universal adhesive, etchant applied enamel-first |
| Gap at the floor | Cold and bite sensitivity, sometimes a radiolucent line | Liner on deep dentine, smaller increments or a low-stress bulk-fill | RMGI liner, SDR Plus |
| Under-cure | Dull ache, sensitivity that does not settle | Light output known; tip close; cure from more than one direction | Curing light within its stated irradiance |
| Contamination | Marginal staining, sensitivity, early debond | Rubber dam; re-etch contaminated enamel | Rubber dam kit |
| Inflamed pulp before treatment | Lingering pain, history of sensitivity | Vitality test; liner or calcium silicate; warn the patient | Calcium hydroxide or calcium silicate liner |
| Cracked cusp | Pain on release of bite | Bite test before treatment | None; treatment plan changes |
The chairside checklist
- Vitality and bite test on any deep or previously restored tooth.
- Rubber dam on, or a dry retracted field with fresh rolls.
- Etch enamel first; keep dentine etch short; rinse; leave dentine moist.
- Liner or desensitiser on the deepest dentine when the cavity is within a millimetre or two of the pulp.
- Adhesive scrubbed in, solvent evaporated until the film stops moving, cured for the full time.
- Increments no thicker than the material's stated depth of cure; bulk-fill only to 4 mm, capped.
- Cure from the occlusal and, on a deep box, from buccal and lingual after the matrix is removed.
- Articulating paper in centric and excursions; adjust; polish.
- Tell the patient what mild sensitivity looks like and what needs a call.
Recommended products: the sensitivity-prevention kit
Liners and desensitisers for the deep dentine step:
The materials that remove the other causes: a low-stress bulk-fill, a light that cures to depth, thin articulating paper and isolation:
Buying advice
If the clinic has none of these, start with a resin-modified glass ionomer liner and a box of thin articulating paper; between them they address the two most frequent causes. Add a desensitiser for bleaching and sensitive patients, and check the curing light's output before buying a bulk-fill that depends on it.
Frequently asked questions
How long is sensitivity after a filling normal?
Mild cold sensitivity that fades over days to a few weeks is common and usually settles as the pulp recovers and the dentine seals. Sensitivity that gets worse, pain on biting, or pain that lingers after the stimulus is removed needs the restoration checked for a high spot, a gap or a crack.
Does a liner reduce sensitivity?
A resin-modified glass ionomer or a calcium-hydroxide liner over the deepest dentine reduces the number of open tubules under the restoration and keeps the etchant and adhesive off the thinnest dentine. It does not compensate for over-etching or an under-cured composite elsewhere in the cavity.
Should I use a desensitiser under every composite?
Not routinely. Desensitisers are useful on deep dentine, on patients with a history of sensitivity, and after bleaching. Applying them everywhere adds a step and can interfere with some adhesives; follow the adhesive's instructions on compatible desensitisers.
Is bulk-fill more or less likely to cause sensitivity?
Systematic reviews of clinical trials found no significant difference in post-operative sensitivity between bulk-fill and incrementally placed composites. A bulk-fill placed deeper than its stated depth of cure, or cured with a weak light, is the risk, not the class itself.
What if the tooth is sensitive to bite but the occlusion is fine?
Check for a gap at the cavity floor or margin (a wedge under the restoration in the radiograph, a catch with the explorer) and for a cracked cusp with a bite test on each cusp. A gap usually means the restoration must be replaced; a crack changes the treatment plan.
Sources
- Causes and solutions for post-operative sensitivity, Dental Products ReportPractice
- Post-op sensitivity after composite fillings, Dentsply Sirona clinical resourceManufacturer
- Bulk-fill versus incremental layering of direct composite restorations: systematic reviewEvidence
- Selective enamel etch and self-etch modes of universal adhesives: systematic review and meta-analysisEvidence